
































Body · Lipoedema
Lipoedema in Thessaloniki and Athens, Greece: diagnosis, stages and treatment
This guide is for women who suspect they have lipoedema (lipedema) or have already been diagnosed. I explain how the condition is recognised, how it differs from obesity, what causes it, what conservative treatment can achieve and when surgery is needed. I have been treating lipoedema since 2013.

Medically reviewed by Dr Prodromos Papaioannou, Plastic Surgeon, HESPRAS member, ASPS International Member · Last reviewed:
 Before
 After
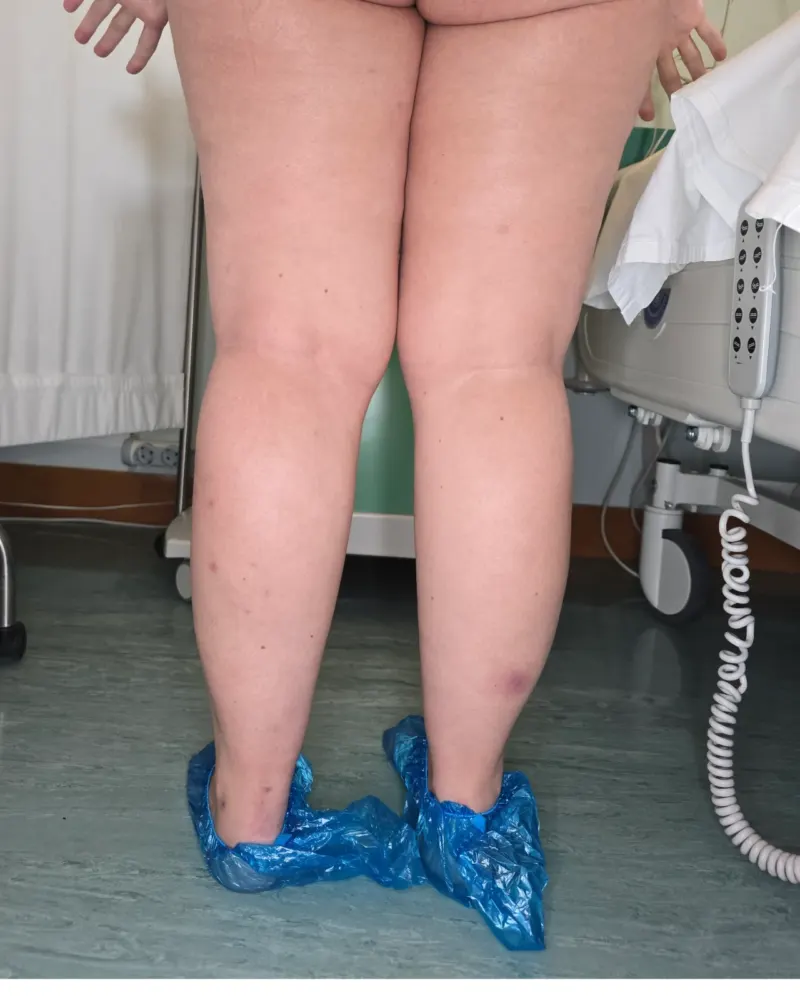 Before
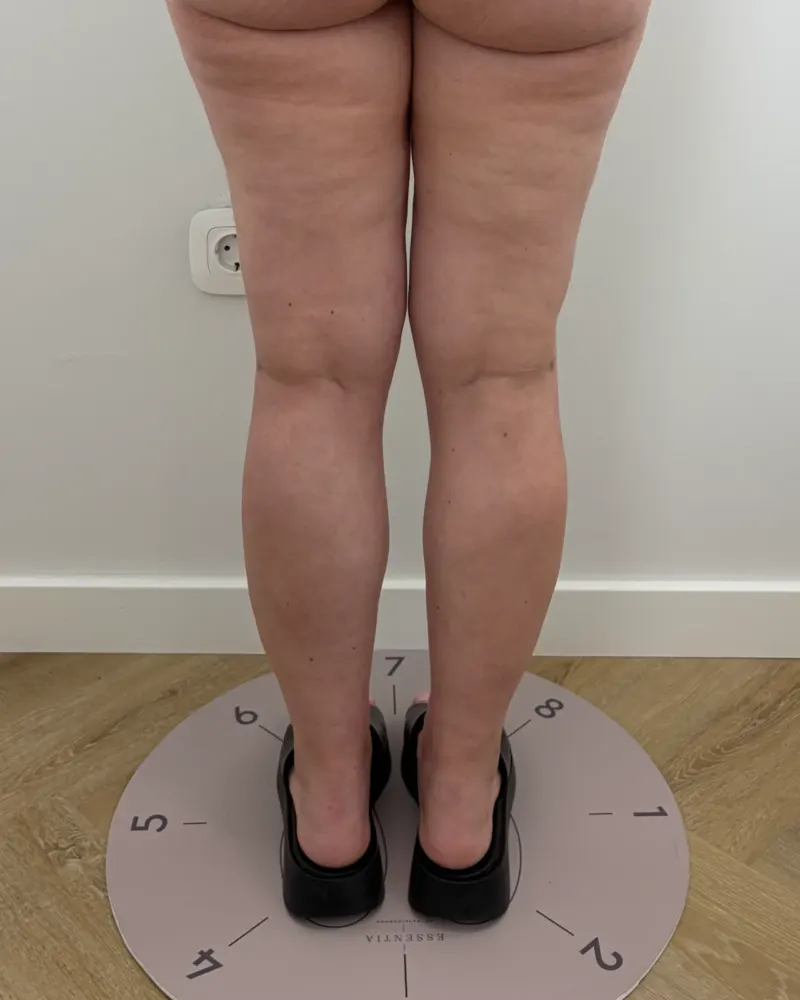 After
These photos include nudity.
Front
Liposuction
Woman, 30–35 · Liposuction · 10 months after · Surgeon: Dr Prodromos Papaioannou
Contact usSee this case →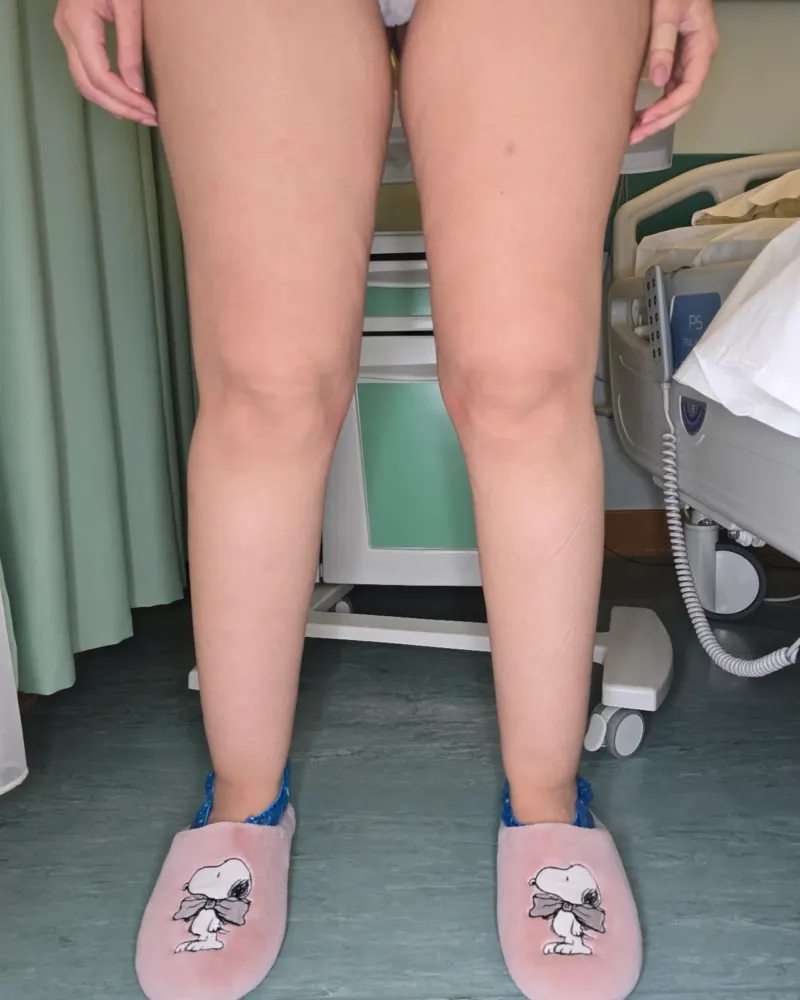 Before
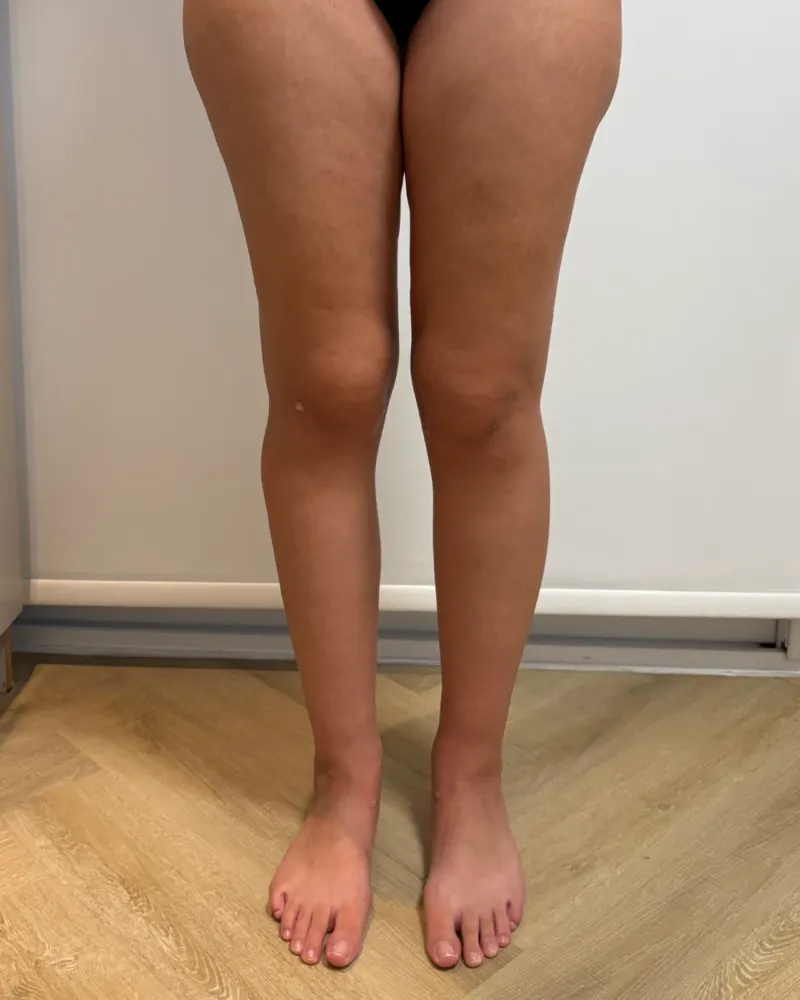 After
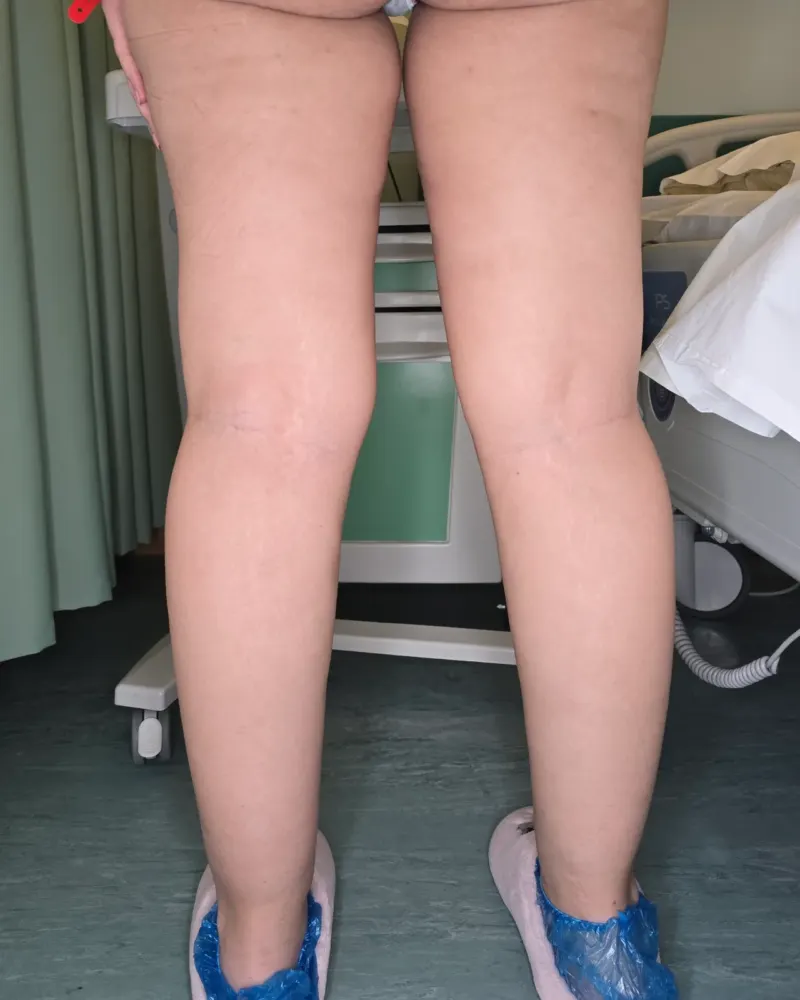 Before
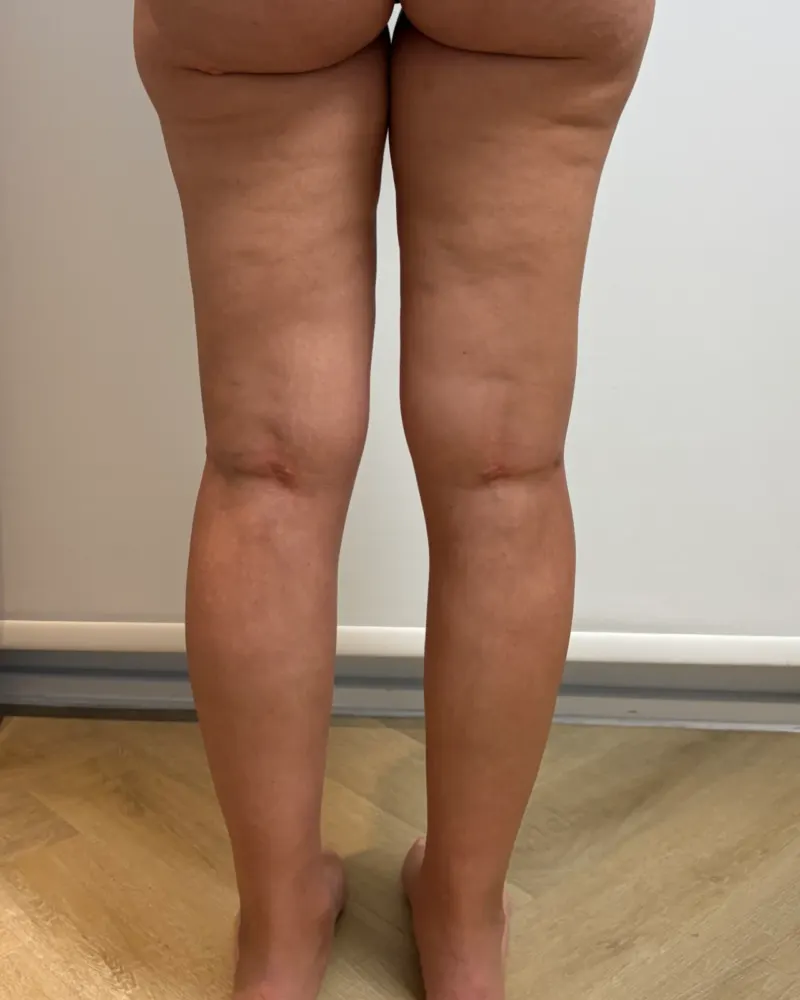 After
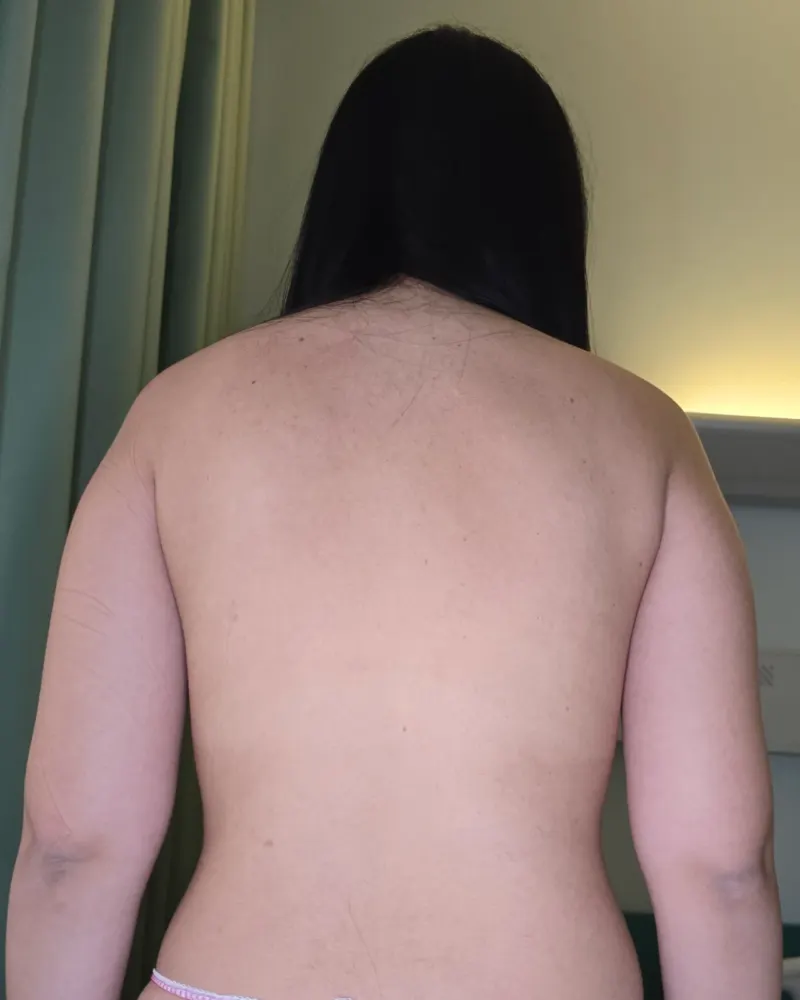 Before
 After
These photos include nudity.
Front
Liposuction for lipedema
Woman, 25–30 · Liposuction for lipedema · 11 months after · Surgeon: Dr Prodromos Papaioannou
Contact usSee this case →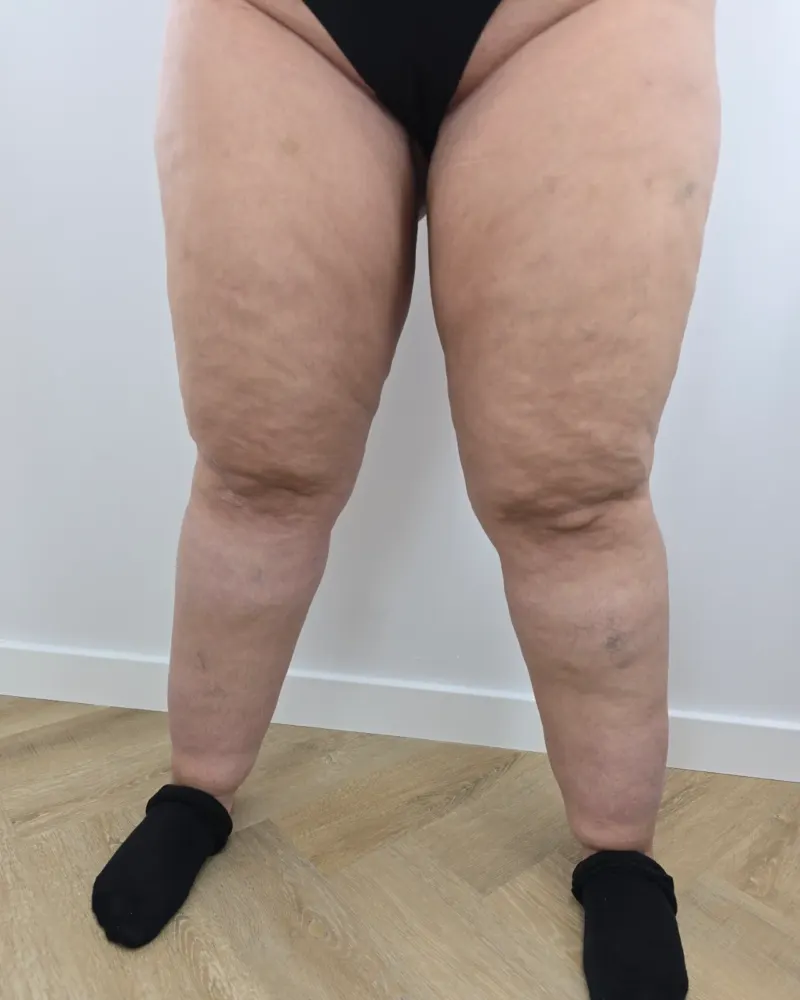 Before
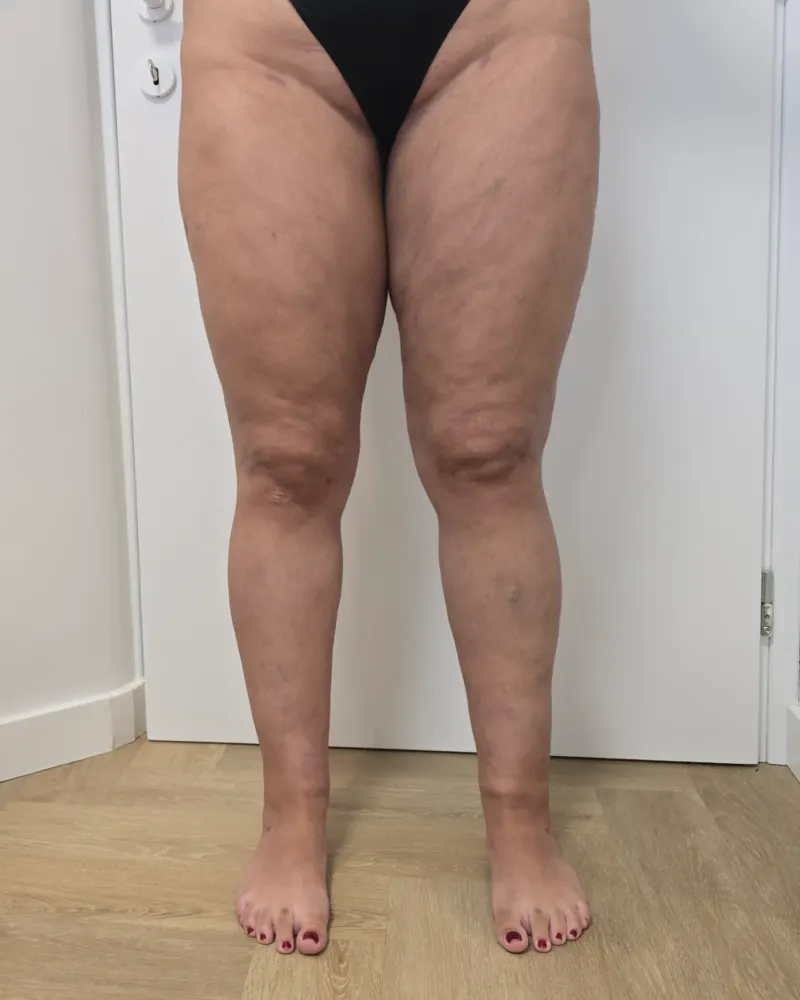 After
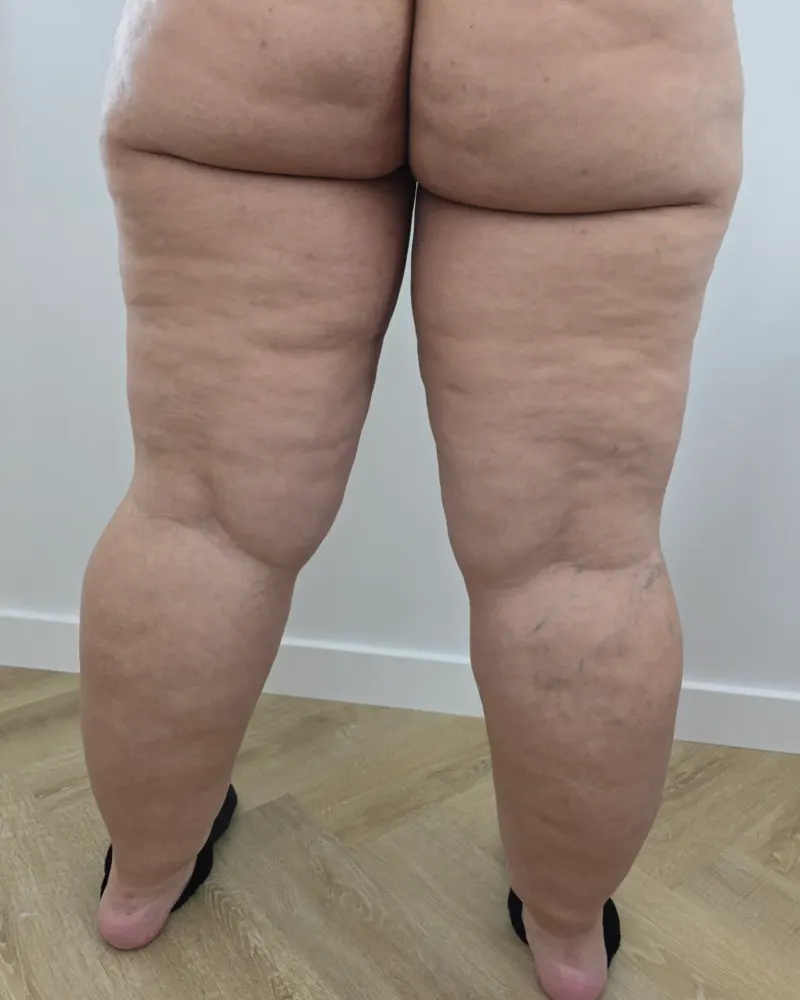 Before
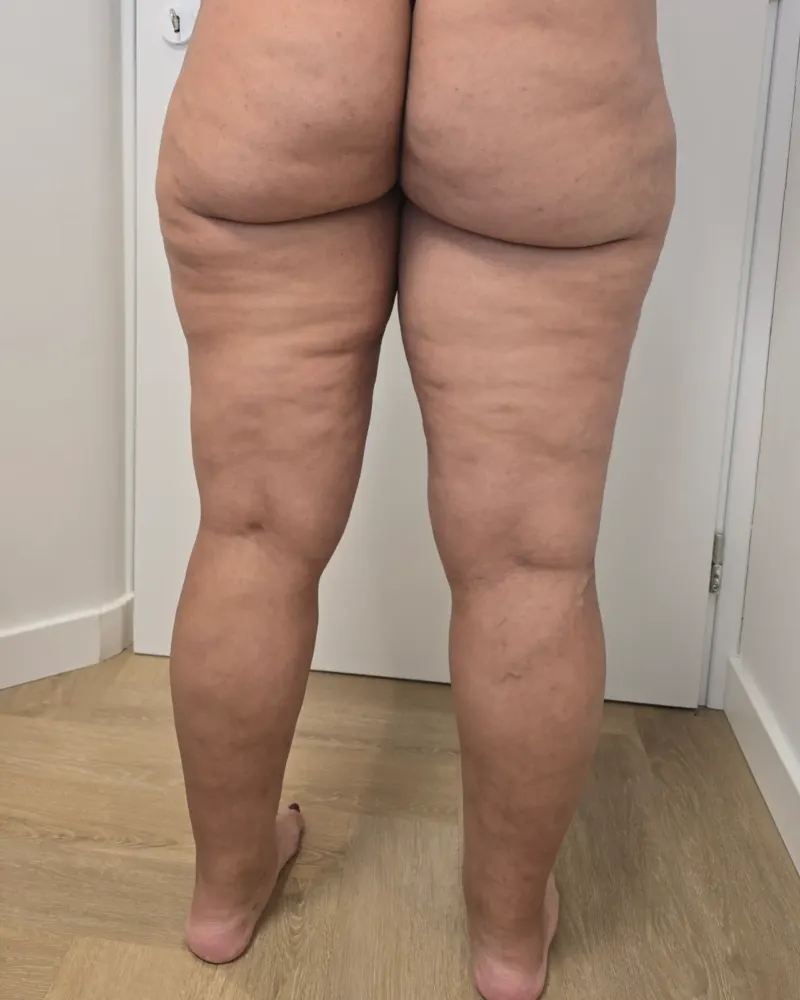 After
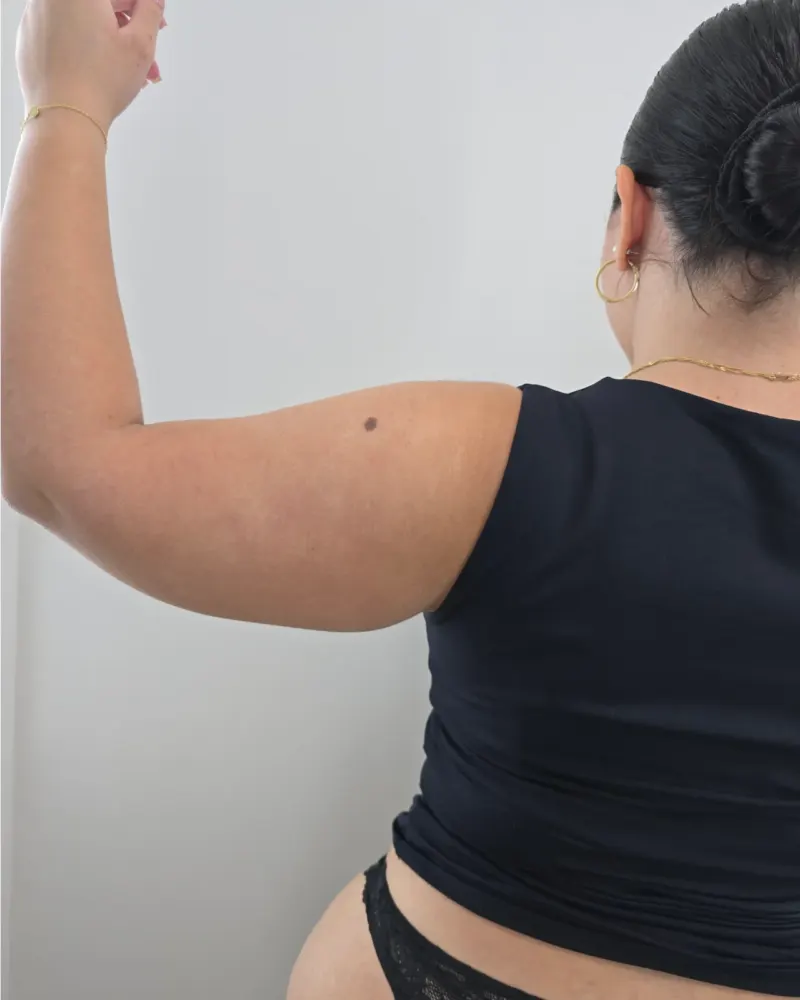 Before
 After
These photos include nudity.
Front
Liposuction for lipedema and liposuction
Woman, 25–30 · Liposuction for lipedema and liposuction · 8 months after · Surgeon: Dr Prodromos Papaioannou
Contact usSee this case →Results vary from patient to patient.
What is lipoedema?
Lipoedema is a chronic condition of the fatty tissue that affects almost only women. Fat builds up symmetrically and out of proportion in the legs, and often the arms, while the trunk, hands and feet stay slim. The fat is painful to pressure, bruises easily and does not go with diet or exercise.
The condition was first described in 1940 by Allen and Hines at the Mayo Clinic. How common it is remains unclear: estimates reach about 10% of women, but the data are limited.
In practice, lipoedema is often mistaken for obesity, lymphoedema or simply an inherited body shape. Many women have been told “that is just how you are built” and have spent years dieting without any change in the shape of their legs. Most of the patients who come to my practice were not referred by another doctor; they read about the condition and recognised the symptoms themselves.
Studies describe a chronic inflammatory disorder of the fat, with changes in the small blood vessels and lymphatic vessels. The fat cells enlarge and fluid leaks into the space between the cells, which explains the heaviness and swelling. The exact mechanism is not yet understood.
The diagnosis is clinical: it rests on examination and history, and no blood test or scan confirms it. Lipoedema cannot be cured for good, but it can be controlled. The 2024 German guideline notes that it does not progress in every woman and can stay stable for years when body weight stays stable.
How do I know if I have lipoedema?
Two features make the diagnosis likely: a mismatch between a slim trunk and fuller limbs, and pain or tenderness in the fat of the limbs. If the fat on your legs does not respond to diet, hurts when pressed and bruises easily, it is worth being examined by a doctor experienced in lipoedema.
The symptoms
- Disproportion: the trunk and waist are slimmer than the legs or arms, and clothing sizes often differ between top and bottom.
- Pain: on pressure, on touch or without any trigger, felt as burning, stinging or heaviness. It gets worse after long periods of standing.
- Heaviness and swelling in the legs, worse in the evening and in summer.
- Easy bruising with no known knock, in some patients.
- Resistance to dieting: weight comes off the face and trunk, but the legs stay the same.
- Uneven skin texture that looks like marked cellulite, with small nodules felt under the skin. Cellulite on its own does not mean lipoedema.
Many patients first see an orthopaedic surgeon for knee pain, and no orthopaedic cause is found. Venous insufficiency often coexists. Lipoedema usually starts at puberty or after a pregnancy.
Where it appears
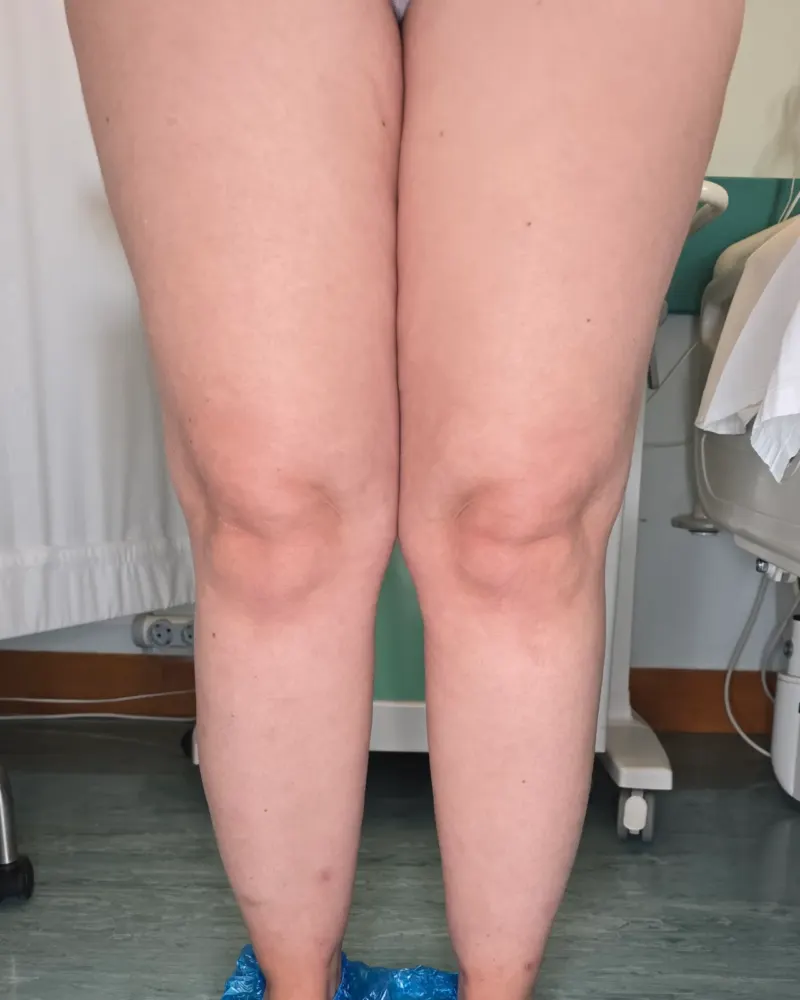
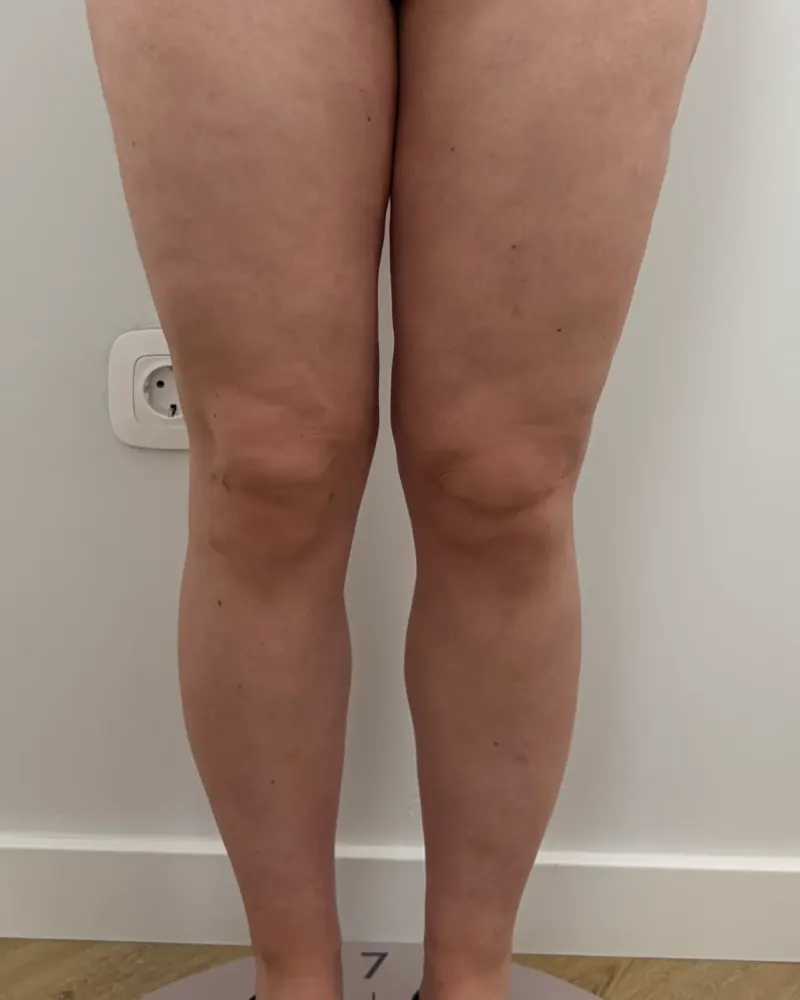
The most typical area is the knee: a “cushion” of fat on the inner side and a calf that runs into the thigh in one continuous, “one-piece” line. Fat also builds up on the thighs, hips and calves down to the ankle, and often on the arms. The feet and hands stay slim.
Most women recognise the symptoms themselves first. At the consultation I confirm the diagnosis and separate it from obesity, lymphoedema and venous insufficiency, with thyroid tests and a venous ultrasound scan when needed.
What are the stages and types of lipoedema?
Lipoedema is divided into 4 stages, according to how the skin and fat look, and into 5 types, according to the areas involved. The stage can differ from one area to another; a patient is usually classified by her most advanced area.
| Stage | What we see | What it means for treatment |
|---|---|---|
| 1 | Smooth skin, disproportion, small nodules, a “one-piece” look at the knees and ankles | Conservative care and stable weight; liposuction when there are symptoms or progression |
| 2 | Uneven, dimpled skin, larger nodules, pain, bruising, swelling after standing | Liposuction also has a functional aim: less pain and heaviness |
| 3 | Large masses of fat, hard nodules, folds around the knees, difficulty walking | Usually more than one operation, alongside weight loss |
| 4 (lipolymphoedema) | The lymphatic system is also affected, with a lymphoedema-like picture and skin changes | Permanent compression; more limited, targeted fat removal |
According to the 2024 German guideline, the stage describes appearance, not the intensity of symptoms: a woman with stage 1 lipoedema may have more pain than a woman with stage 3.
The 5 types describe the areas involved:
- Type I: buttocks and hips.
- Type II: from the hips to the knees.
- Type III: from the hips to the ankles.
- Type IV: the arms, usually together with the legs.
- Type V: the calves only.
The type does not indicate severity. It does help us plan which areas need treatment and in what order, if more than one operation is needed.
Is it lipoedema or obesity?
They are two different conditions that often occur together. Obesity increases fat all over the body and goes down with weight loss. Lipoedema affects the limbs symmetrically, is painful and stays despite dieting. Many women have both, which is why telling them apart is the first step in deciding what treatment can and cannot change.
| Lipoedema | Obesity | |
|---|---|---|
| Distribution | Legs and arms, with a slim trunk, feet and hands | The whole body, often mainly the abdomen |
| Pain and bruising | Common | Usually not |
| With dieting | Weight comes off the trunk, not the limbs | Fat goes down everywhere |
| Onset | Often at hormonal changes: puberty, pregnancy, menopause | At any age |
| Sex | Almost only women | Men and women |
BMI (body mass index) is misleading in lipoedema, because the weight of the legs pushes it up without obesity necessarily being present. I therefore also measure waist circumference in relation to height, which reflects fat on the trunk better. The 2024 German guideline recommends using the two together.
When both are present, a vicious cycle forms: extra weight makes lipoedema worse, while pain and heaviness in the legs make exercise harder and failed diets take a psychological toll. Weight does not cause lipoedema, but it is the most important factor that makes it worse. It has not been shown that lipoedema itself raises the risk of obesity.
In practice, absolute weight does not show how severe lipoedema is. I see women of normal weight with stage 2 or 3 lipoedema and overweight women with mild lipoedema. At stage 4, however, obesity is almost always present. Weight loss improves the part due to obesity, but the lipoedema tissue remains. That is why an accurate diagnosis matters: it shows what diet can change and what it cannot.
What causes lipoedema?
The exact cause is not known. The two factors with the most evidence are heredity and the hormonal changes of a woman’s life, while body weight affects how severe it becomes. Lipoedema is not caused by overeating or a lack of willpower, and no diet is certain to prevent it.
Heredity
Lipoedema often affects several women in the same family. In reviews, up to 60% of patients report a first-degree relative with the condition, but this does not mean a 60% chance of passing it to a daughter; the exact risk is not known. The pattern looks autosomal dominant with incomplete penetrance. There is no genetic test or blood test that confirms the diagnosis.
Hormonal changes: puberty, pregnancy and menopause
Lipoedema almost always starts or worsens at times of hormonal change. It usually first shows at puberty, with disproportion on the thighs, the buttocks and around the knees. Many women describe a marked worsening in pregnancy, often the second or third, with rapid weight gain despite careful eating. In perimenopause and menopause lipoedema can also get worse, together with weight gain. Some patients link the worsening to fertility treatment, contraceptives or gynaecological surgery.
A role for female hormones is assumed, because the condition affects almost only women and starts at hormonal transitions; the German guideline notes, however, that there are no reliable data on the hormonal profile of patients. There is no evidence that pollution or stress cause lipoedema. An underactive thyroid and type 2 diabetes are checked and brought under control before any treatment.
What can conservative treatment do for lipoedema?
Conservative treatment relieves the pain, heaviness and swelling of the legs and helps keep weight stable, so that lipoedema does not progress. It does not, however, remove the lipoedema tissue or meaningfully change the shape of the limbs. It is needed at every stage, before and after any surgery.
At the lipoedema practice at Interbalkan Medical Center I work with physiotherapists and dietitians, so that each woman has a plan suited to her stage, her weight and her daily life.
Compression and lymphatic drainage
Compression stockings or tights, ideally with a special knit for lipoedema and made to measure, reduce swelling and heaviness, and many women have less pain. Lymphatic drainage by a certified physiotherapist brings relief when there is oedema. Avoiding long periods of standing also helps. In reviews, limb volume falls only a little (about 5–10%), while tenderness and tightness improve.
Exercise and weight control
A stable weight is the most important non-surgical way to keep lipoedema from getting worse. In my experience, once weight has risen a lot, lipoedema rarely returns to how it was before, even if the weight comes off. The joints cope best with a stationary bike, an elliptical trainer, a rowing machine and exercise in water, at moderate intensity. For major weight loss, medication or bariatric surgery can help, after assessment by an endocrinologist.
Diet
No specific lipoedema diet has been proven in randomised trials; diet aims to control weight and inflammation, not to make lipoedema disappear. I recommend little sugar and few refined carbohydrates, enough protein, vegetables and olive oil. Low-carbohydrate diets have shown benefit in small studies. Avoiding gluten or dairy makes sense only if you are intolerant. The dietitian draws up the plan.
In short, conservative treatment changes how you feel, but it does not remove the abnormal fat. When symptoms persist or the condition progresses, the next step is surgery.
When is surgery needed for lipoedema?
I recommend surgery when pain, heaviness or swelling persist, or when lipoedema progresses despite conservative treatment. Liposuction is currently the only treatment that removes lipoedema tissue. It controls the condition and limits its progression for many years, but it does not cure it for good.
I use a lymph-sparing technique: infiltration of a local anaesthetic (tumescent) solution and, mainly, power-assisted liposuction (PAL), with gentle movements along the length of the limb. In selected cases I use water-assisted liposuction (WAL). Conventional liposuction without these precautions can damage the lymphatic vessels, which in lipoedema are already under strain.
The number of operations depends on severity, but mainly on body weight:
- Up to about 70 kg: treatment is usually completed in one operation.
- 70 to 90 kg: two are usually needed.
- Over 90 kg: I recommend losing weight first, especially when BMI is above 40 and the waist-to-height ratio above 0.55; if that is not possible, more than two operations may be needed.
In each operation I usually remove no more than 7 litres, so that recovery stays safe. Before surgery, thyroid function, diabetes and any anaemia must be under control, and weight must be stable. I do not operate during pregnancy or breastfeeding.
After surgery, conservative care continues, usually to a lesser degree. You wear a special lipoedema compression garment for 3 to 6 months and have lymphatic massage from the second week, 2 to 3 times a week for 3 months. Pain, bruising and heaviness usually improve within the first months, and studies with follow-up of up to 12 years show that the improvement lasts.
I explain the technique, preparation, week-by-week recovery and risks in detail on the page Liposuction for lipoedema. If loose skin remains after fat removal, mainly on the thighs or arms, it is treated as described on the page Loose skin after lipoedema treatment.
Frequently asked questions
Is lipoedema hereditary?
Yes, there is a clear inherited predisposition. Other women in the family often have the same body shape, and in reviews up to 60% of patients have a first-degree relative with lipoedema. The predisposition does not show in everyone, though: it also depends on hormonal changes and body weight. If your mother has lipoedema, it does not mean you will develop it too. It means it is worth watching your weight, especially at puberty, in pregnancy and at menopause, and being examined early if symptoms appear. There is not yet a genetic test for the diagnosis.
Can lipoedema be cured permanently?
Not permanently, but it can be controlled. Conservative treatment relieves the symptoms, and liposuction removes most of the abnormal tissue. After surgery, the improvement in pain, swelling and bruising lasts for many years, and most women need less conservative care than before. Lipoedema can return to some degree, mainly with major weight gain or hormonal changes. The right question is not whether it will come back, but how far it would have progressed without treatment. I explain the results on the page Liposuction for lipoedema.
Will my health insurance cover lipoedema treatment?
Lipoedema surgery is one of the procedures that insurers may cover, and the practice provides a medical letter for your insurer. In general, insurers ask for a documented diagnosis, a description of the symptoms and stage, and a record of the conservative treatment already tried. After the consultation I give you a written medical report with the diagnosis, the stage in each area and the proposed plan, which you can send to your insurer. You need to confirm cover directly with your insurer before surgery.
Can you have lipoedema if you are slim?
Yes. Lipoedema is not about total weight but about where the fat sits. I often see women of normal or low weight, with a slim waist and trunk, who have disproportionate legs, pain on pressure and easy bruising, and even stage 2 or 3 lipoedema. In these women, dieting usually slims the face and chest without changing the legs. That is why the diagnosis is made by examination and history, not by the scales or BMI. A stable weight still matters in these cases.
Do weight-loss injections help lipoedema?
Weight-loss medicines reduce overall weight, but they have not been shown to reduce the lipoedema tissue itself. In women with both lipoedema and obesity, they can help reach a weight at which liposuction is safer and more effective, with fewer operations. Weight loss often shows more on the trunk and less on the legs, so the disproportion can become more noticeable. They should always be used after assessment by an endocrinologist or another appropriate doctor.
Which doctor diagnoses lipoedema?
A doctor experienced in lipoedema can make the diagnosis: a plastic surgeon, a vascular surgeon, a dermatologist specialising in phlebology, or a lymphologist. The diagnosis is clinical, by examination and history; no blood test or scan confirms it. Tests are used to rule out other causes of swelling or weight gain, such as an underactive thyroid, venous insufficiency, lymphoedema, or heart or kidney disease. At the consultation I examine each area separately, because the stage can differ, and we discuss whether conservative treatment is enough or surgery is needed.
Can I have liposuction for lipoedema if I want children later?
Yes, liposuction does not affect fertility or pregnancy. Pregnancy is, however, one of the times when lipoedema can get worse, and major weight gain can reduce part of the benefit of surgery. I do not operate during pregnancy or breastfeeding. I usually advise waiting at least 6 months after the birth and after breastfeeding ends, with a stable weight; if you plan more pregnancies, surgery is ideally done once they are complete. In any case, a stable weight and conservative care during pregnancy help to preserve the result.
References
- Faerber G, Cornely M, Daubert C, et al. S2k guideline lipedema. J Dtsch Dermatol Ges. 2024;22(9):1303-15. PMID: 39188170. doi:10.1111/ddg.15513.
- Herbst KL, Kahn LA, Iker E, et al. Standard of care for lipedema in the United States. Phlebology. 2021;36(10):779-96. PMID: 34049453. doi:10.1177/02683555211015887.
- Kruppa P, Georgiou I, Biermann N, Prantl L, Klein-Weigel P, Ghods M. Lipedema: pathogenesis, diagnosis, and treatment options. Dtsch Arztebl Int. 2020;117(22-23):396-403. PMID: 32762835. doi:10.3238/arztebl.2020.0396.
- Buso G, Depairon M, Tomson D, Raffoul W, Vettor R, Mazzolai L. Lipedema: a call to action! Obesity (Silver Spring). 2019;27(10):1567-76. doi:10.1002/oby.22597.
- Child AH, Gordon KD, Sharpe P, et al. Lipedema: an inherited condition. Am J Med Genet A. 2010;152A(4):970-6. PMID: 20358611. doi:10.1002/ajmg.a.33313.
- Baumgartner A, Hueppe M, Meier-Vollrath I, Schmeller W. Improvements in patients with lipedema 4, 8 and 12 years after liposuction. Phlebology. 2021;36(2):152-9. doi:10.1177/0268355520949775.
- Allen EV, Hines EA Jr. Lipedema of the legs: a syndrome characterized by fat legs and orthostatic edema. Proc Staff Meet Mayo Clin. 1940;15:184-7. doi:10.1016/S0025-6196(25)37697-4.
Consultation
In Thessaloniki, in Athens or by video. Examination, options and a written plan.