
































Body · Lipoedema
Liposuction for lipoedema in Thessaloniki and Athens, Greece
I perform more than 50 liposuctions for lipoedema a year and have been a specialist plastic surgeon since 2012. At the lipoedema practice at Interbalkan I work with physiotherapists and dietitians, so that surgery is one part of an overall treatment plan rather than a stand-alone procedure.
Liposuction for lipoedema (lipedema) removes the diseased fat tissue from the legs and arms with a technique that protects the lymphatic vessels. It is for women whose lipoedema causes symptoms or keeps progressing despite conservative treatment. It reduces pain, heaviness and swelling, although it does not cure the condition permanently.
50+
operations a year

At a glance
What it treats
Lipoedema fat on the thighs, knees, calves, ankles and upper arms; pain, heaviness and swelling of the limbs
Anaesthesia
General, combined with a local anaesthetic (tumescent) solution
Operating time
Usually 2 to 4 hours, depending on the volume
Hospital stay
Usually 1 night; often spread over 2 or more operations
Back to work
10 to 15 days for desk work; about 1 month for work on your feet
Exercise
Walking from day one; exercise after the first month
Final result
3 to 6 months above the knee; 6 to 12 months for the calves and ankles
Where
Interbalkan Medical Center, Thessaloniki
Medically reviewed by Dr Prodromos Papaioannou, Plastic Surgeon, HESPRAS member, ASPS International Member · Last reviewed:
What is liposuction for lipoedema?
Liposuction for lipoedema (radical subcutaneous lipectomy) removes the diseased fat of the limbs through fine cannulas, after the tissue has been filled with a local anaesthetic solution (tumescent). It is the only treatment that removes lipoedema tissue. It does not cure the condition permanently, but it reduces the symptoms for many years.
It is a different operation from cosmetic liposuction. Much larger volumes are removed, often more than 5 litres (mega-liposuction), and the technique has to protect the lymphatic vessels, which in lipoedema are already under strain. For an overview of the condition itself, see the page on lipoedema.
Is liposuction for lipoedema right for you?

It suits women with diagnosed lipoedema who have pain, heaviness or swelling in the limbs, or who see the condition progressing, despite compression stockings, lymphatic drainage massage and diet. You need a stable weight and a willingness to keep up conservative care afterwards. Whether it is right for you is always decided at the examination.
In stages 1 and 2 we usually start with conservative treatment: lymphatic drainage massage, compression stockings, exercise and a tailored diet. These ease the swelling but do not remove the tissue. Symptoms do not always match the stage, so I also operate on stage 1 lipoedema when symptoms persist. Conservative care continues after surgery, to a lesser degree.
Who is a typical candidate?
- Pain, a feeling of heaviness or swelling that conservative treatment does not adequately relieve.
- Lipoedema that is spreading or limits movement, mainly around the knees.
- Marked disproportion between the trunk and the limbs, which makes choosing clothes difficult in practice.
- Stage 1 lipoedema, where surgery improves the contour and limits progression.
When do I not recommend it?
- When the main problem is obesity, for example with a BMI above 40 and a waist-to-height ratio above 0.55; weight loss then comes first.
- When your weight has not yet stabilised.
- During pregnancy and breastfeeding.
- When there is uncontrolled heart disease, another serious condition or anaemia that rules out large-volume surgery.
- When you cannot set aside the recovery time, the compression garments and the lymphatic drainage massage needed after surgery.
What happens at the consultation, and how do I prepare?
At the consultation I confirm the diagnosis, examine each area and plan how much fat to remove, in how many operations and in what order. Before surgery you need blood tests with attention to haematocrit and iron, an anaesthetic assessment and, where needed, a venous ultrasound. You stop smoking 4 weeks before and after.
What happens at the consultation?
I confirm the diagnosis and distinguish it from obesity, lymphoedema and venous insufficiency, which often coexist. I examine each area separately, because the stage can differ from one area to another, and I assess your weight and skin quality. I estimate the volume of fat, whether one operation is enough and in which order the areas will be treated. We discuss a realistic result and the programme of compression and lymphatic drainage massage. You receive a written plan.
What tests and instructions apply before surgery?
You need pre-operative blood tests, with particular attention to haematocrit and iron, because the operation is followed by a drop in haematocrit; if you are iron deficient, we correct this first. You are assessed for general anaesthesia and, where needed, have a venous ultrasound scan by a vascular surgeon. Smoking increases the risk of complications: stop at least 4 weeks before and 4 weeks after surgery. If you take anticoagulants or antiplatelet medicines, tell me; they are only stopped in agreement with the doctor who prescribes them. The date is set once the tests are complete, at a time without pressing work or family commitments.
How is liposuction for lipoedema performed?
The operation is done under general anaesthesia, with a local anaesthetic solution injected into the fat. I prefer power-assisted liposuction (PAL), with gentle movements that protect the lymphatic vessels. I usually remove up to 7 litres per session; when there is more to remove, treatment is planned as two or more operations.
First I infiltrate a saline solution containing a local anaesthetic and an agent that limits bleeding (tumescent). I then remove the fat with fine cannulas through small incisions. The duration depends on the volume and the areas treated, usually 2 to 4 hours. You often need to lie face down; this is why I prefer general anaesthesia, which allows large volumes and safe control of breathing.
Why do I protect the lymphatic vessels during surgery?
In lipoedema the lymphatic system is already under strain; the more intact the lymphatic vessels remain, the faster the swelling settles. The tumescent solution expands the tissue and keeps the cannula away from the vessels, with less damage than the “dry” technique. The cannula moves parallel to the lymphatic vessels.
Power-assisted (PAL) or water-assisted (WAL) liposuction?
In my practice power-assisted liposuction (PAL) is the main technique. The vibration of the cannula reduces resistance and tissue trauma, and allows large volumes to be removed in less time, with precise contouring. Water-assisted liposuction (WAL) is also atraumatic and suitable, but it takes longer and introduces more fluid, with more marked swelling in the first hours; I use it in selected cases.
One operation or more?
In women weighing up to 70 kg, treatment is usually completed in one operation, and at 70 to 90 kg in two. I do not exceed 7 litres per operation: up to 5 litres recovery is smooth, up to 7 litres it is acceptable, and above 7 litres the likelihood of a blood transfusion rises. At higher body weights I recommend losing weight first. In the first operation I treat the back of the body and in the second the front, 3 to 6 months apart.
Strategy by stage
- Stage 1: the approach is mainly aesthetic, with better curves at the calves, ankles and thighs. On average 3 to 5 litres are removed, and the aim is also to stop the condition from progressing.
- Stage 2: symptoms are now present, so surgery is also functional. Usually 4 to 6 litres are removed.
- Stage 3: removal is more extensive, often more than 7 litres, in 2 or more sessions, with the aim of less pain and better knee function. At the same time we work towards weight loss.
- Stage 4 (lipo-lymphoedema): removal is more conservative and focuses on limited areas, such as the knees, because the skin has lost elasticity and blood supply.
Treatment areas
I rarely treat one area in isolation; the limb is treated as a single unit. The knees are the most common area: the inner side, around the kneecap and the back. On the calves and ankles, removal has to taper smoothly towards the foot and bring out the Achilles tendon; this is a technically more demanding area. On the thighs and saddlebags I smooth the contour without over-emptying the area that supports the buttocks. On the upper arms the fat weighs down the lower part of the arm; often this is not skin laxity, and liposuction is enough without an arm lift. Where needed, I extend treatment to the elbows and forearms.
Incisions and stitches
The incisions are a few millimetres long and placed where they are hidden. If skin stitches are used, they are removed at 5 to 7 days.
The operation is usually done on its own, on several areas at once. If loose skin remains on the thighs or upper arms, a thigh lift or an arm lift may be needed later.
Hospital stay
After a moderate removal you go home the same day; after an extensive removal you stay 1 night. In moderate or severe cases you need someone with you for the first 10 days. If you come from another city, you stay near us for 2–5 days for up to 5 litres, 7–10 days for 5–7 litres and more than 10 days above 7 litres. For the journey home: a flight of up to 3 hours, or car travel with a 10-minute stop every 1–2 hours.
What is recovery like, week by week?
The first 10 to 15 days are the most tiring, with weakness, swelling and bruising, and recovery is more demanding than after cosmetic liposuction. You can return to desk work in 10 to 15 days. Areas above the knee settle in 3 to 6 months, and the calves and ankles in 6 to 12 months.
| When | How you feel | What you can do |
|---|---|---|
| Days 1–5 | Weakness and tiring easily because of the drop in haematocrit; mild to moderate pain after the first 24 hours; swelling and bruising increase | Up and about from day one; compression garment day and night; simple painkillers; plenty of fluids and iron-rich foods; on your feet only when necessary |
| Days 6–15 | A low-grade temperature of up to 37.5–38 °C is common; swelling stays stable until day 10 and then starts to go down | From day 10 the garment can come off at night; desk work at 10–15 days, with a footrest |
| Weeks 2–4 | Swelling, tenderness and numbness | Lymphatic drainage massage from week 2–3; standing for up to 30–60 minutes, with 5–10 minutes legs up every half hour; walking for up to 30 minutes at a time |
| Month 1 | 70–80% of the swelling above the knees has gone, but only 40–50% at the ankles | Exercise again, gradually; work that involves long hours standing |
| Week 6 | The thighs and arms feel more comfortable | Compression above the knee no longer needed |
| Months 3–6 | Areas above the knee and the arms take their final shape | Compression below the knee stops at 3 months (longer after extensive surgery); lymphatic drainage massage for up to 3–4 months |
| Months 6–12 | The calves and ankles settle; numbness fades along with the swelling | Normal activity; lymphatic drainage massage as you wish |
Compression garments
Special lipoedema compression garments or compression stockings are essential. For the first 10 days you wear them continuously, day and night; after that you can take them off to sleep. For areas above the knee daily wear lasts 6 weeks, and for areas below the knee 3 months; after extensive surgery it may need to be longer. As the swelling goes down, the original garment loosens and you need a smaller size. In advanced lipoedema or lipo-lymphoedema, compression may be needed permanently, usually at a lower strength than before.
Lymphatic drainage massage
Lymphatic drainage massage speeds up the resolution of swelling. I prefer it to start after week 2 to 3, when the skin is less sensitive and the massage is tolerable, 2 to 3 times a week for 3 to 4 months, always by a certified physiotherapist. Later you can have it whenever you need it, to relieve your limbs.
Standing, work and diet
Standing for long periods keeps fluid in the legs and slows recovery. For the first 10 to 15 days, stand only when necessary. In jobs with long hours on your feet (hairdressing, pharmacy, hospital work), returning before one month is possible, but swelling and numbness take longer to go; the final result does not seem to be affected. In the first month a diet rich in protein and iron helps, with an iron supplement if you are anaemic. After that, the aim is to maintain or lose weight, with strength training and aerobic exercise. Above all, you need patience: recovery moves slowly, over months.
How long do I need to stay in Greece after liposuction for lipoedema?
How long you stay depends mainly on the volume removed. After a moderate removal you leave the hospital the same day; after an extensive one you stay 1 night. If skin stitches are used, they are removed at 5 to 7 days, before you travel. You then stay near us for a period that depends on the volume removed.
As a guide from my practice, the stay near us is 2 to 5 days for up to 5 litres, 7 to 10 days for 5 to 7 litres and more than 10 days above 7 litres. For the journey home I recommend a flight of no more than 3 hours, or travel by car with a 10-minute stop every 1 to 2 hours to keep your legs moving.
Follow-up after you return home is by video call at 10 days, 1 month, 6 months and 1 year. Before you travel, arrange three things at home:
- someone to stay with you for the first 10 days, if your case is moderate or severe;
- a certified physiotherapist for lymphatic drainage massage, 2 to 3 sessions a week from week 2 to 3, for 3 to 4 months;
- spare compression garments in a smaller size, as the swelling goes down.
If you have a second operation, you plan a second trip 3 to 6 months later.
What results can I expect, and how long do they last?
Pain, heaviness and bruising usually improve within the first months, and knee mobility increases. Studies with follow-up of up to 12 years show that the improvement lasts. Lipoedema is not cured permanently, so keeping your weight stable and continuing conservative care remain important.
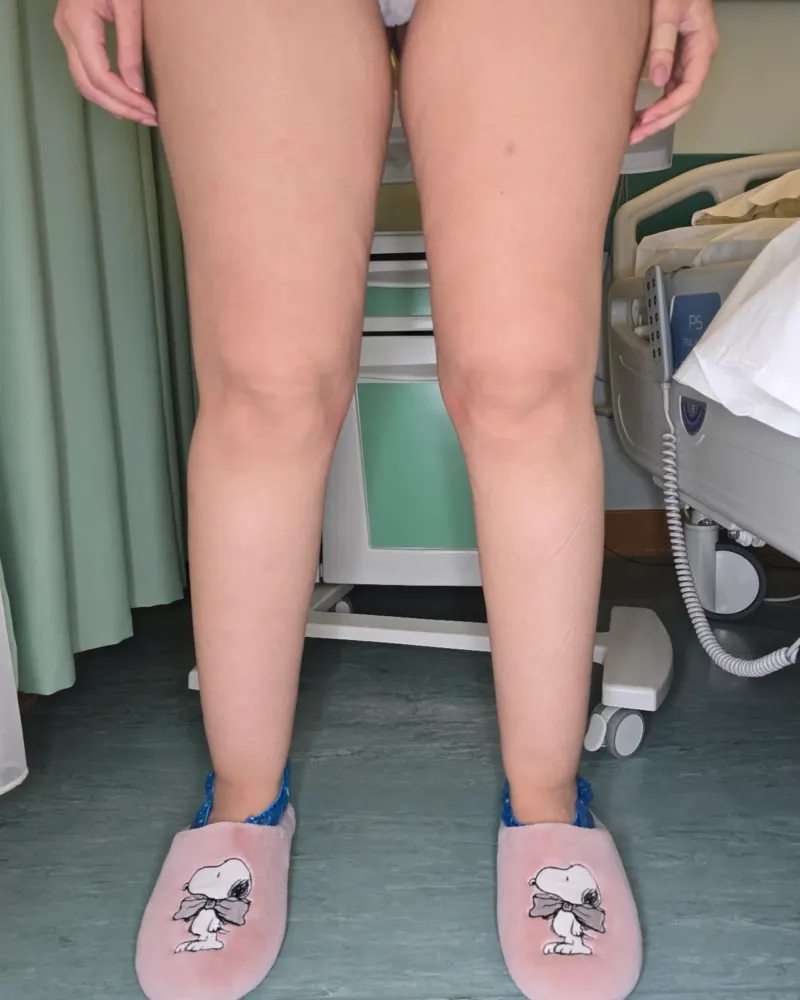 Before
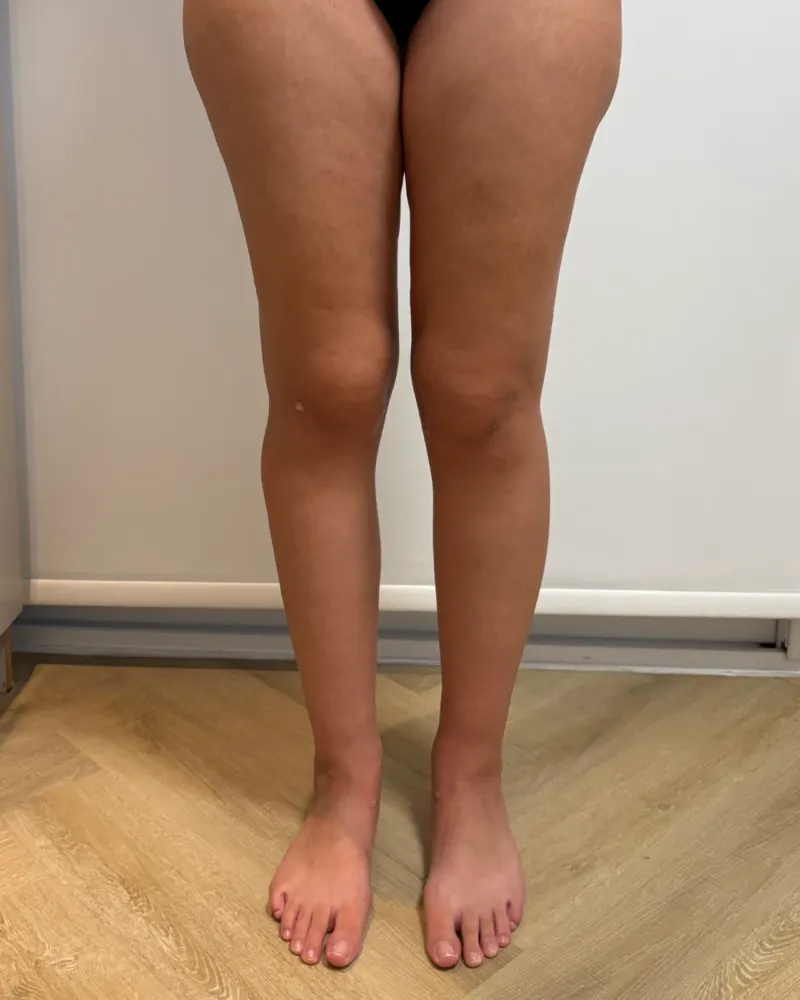 After
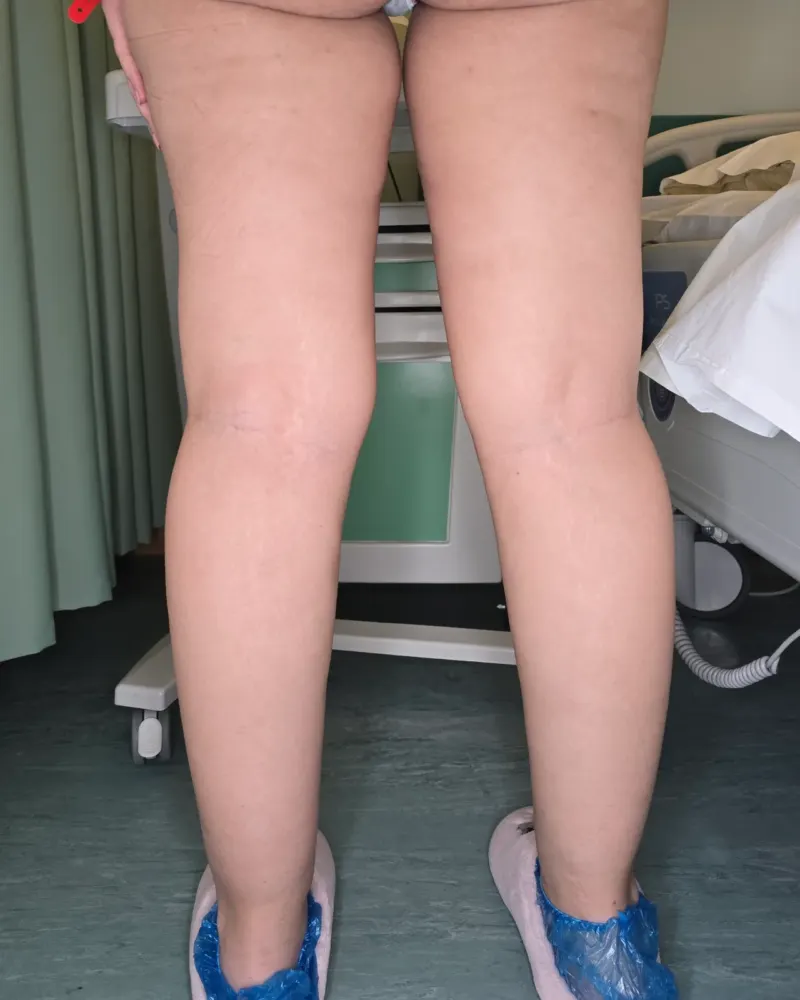 Before
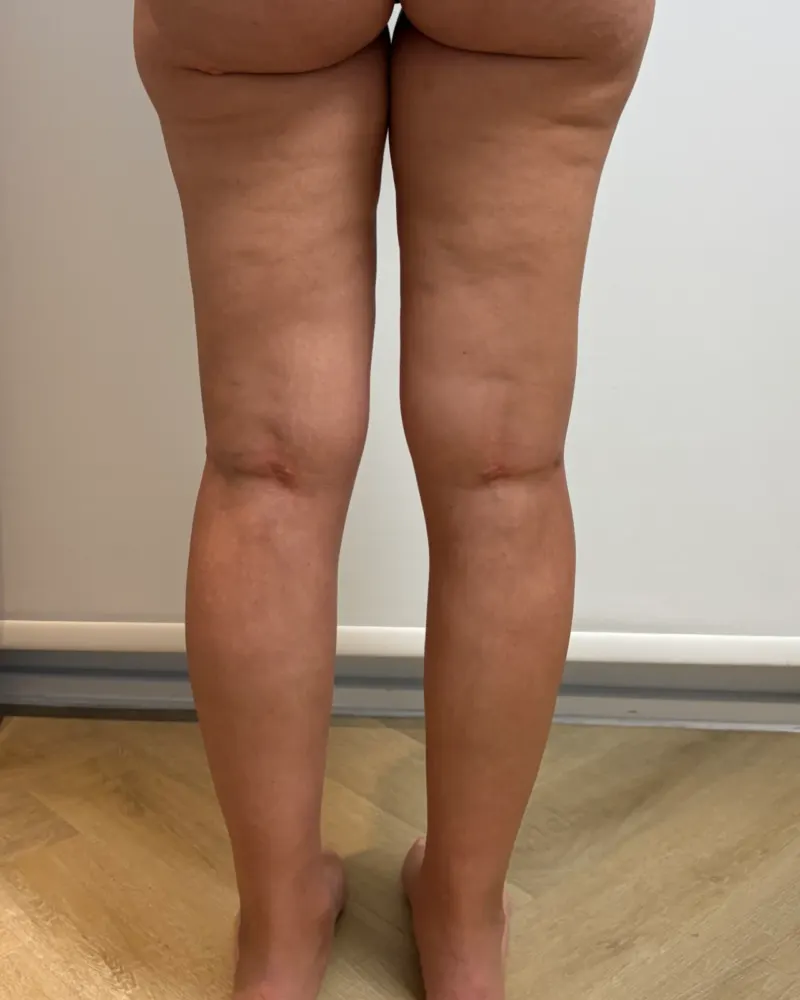 After
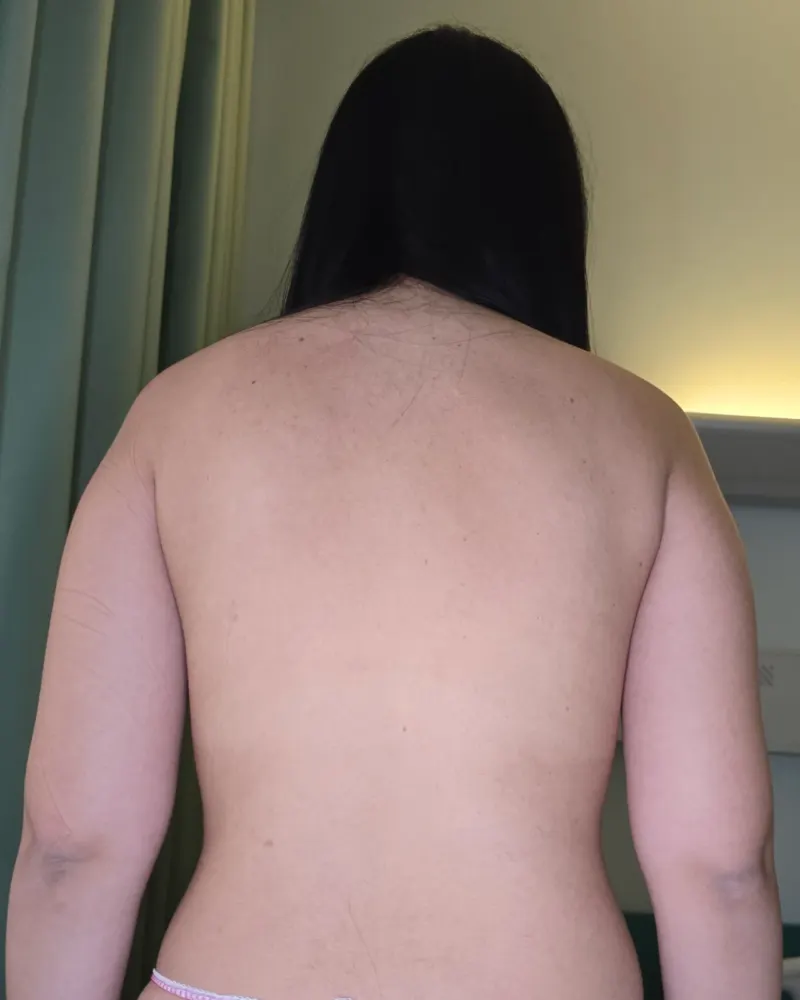 Before
 After
These photos include nudity.
Liposuction for lipedema
Woman, 25–30 · Liposuction for lipedema · 11 months after · Surgeon: Dr Prodromos Papaioannou
Front
Results vary from patient to patient.
By removing most of the diseased tissue, the limb becomes lighter and fat distribution more even: the kneecap is visible again, the ankles regain their contour, and your clothing size matches top and bottom. The cellulite-like appearance is reduced, and with the right technique, leaving an even layer of fat under the skin, liposuction does not cause skin laxity. The scales usually change after the first month, and weight loss can exceed 10 kg. The right goal is not that lipoedema never reappears, but that it does not reach the stage it would have reached without surgery. In the longest studies, patients needed less conservative treatment than before, and results were more durable when surgery was done at an early stage.
What are the risks and complications?
Liposuction for lipoedema is a bigger operation than cosmetic liposuction, because large volumes are removed. The most common difficulties are a drop in haematocrit, prolonged swelling and numbness, all of which settle gradually. Serious complications are rare. I explain the risks for your own case at the consultation.
| Complication | How common | Prevention and management |
|---|---|---|
| Drop in haematocrit, weakness, dizziness | Common, temporary | Up to 7 litres per operation; iron deficiency corrected beforehand; fluids and iron afterwards |
| Need for a blood transfusion | Rare, more likely above 7 litres | Spreading treatment over more operations |
| Prolonged swelling, especially at the calves and ankles | Common, temporary | Lymph-sparing technique, compression garment, lymphatic drainage massage, limited standing |
| Numbness and tenderness | Common, temporary | Settle along with the swelling, even after months |
| Contour irregularities | Uncommon | An even layer of fat under the skin, extra care at the calves; corrected with a minor procedure |
| Loose skin | Not rare with large volumes or at an advanced stage | Correct technique; if needed, a thigh lift or arm lift later |
| Venous thrombosis | Rare | Walking from day one, compression garment, anticoagulant prophylaxis when indicated |
| Infection | Rare | Sterile technique and wound care; antibiotics if needed |
| Worsening of lymphatic function | Rare, with the tumescent technique | Gentle, lymph-sparing movements; conservative removal in lipo-lymphoedema |
Smoking. Stop 4 weeks before and 4 weeks after surgery; smoking increases the risk of thrombosis and slows healing.
Blood thinners. Tell me if you take anticoagulants or antiplatelet medicines. They are always stopped in agreement with the doctor who prescribes them.
What determines the cost of liposuction for lipoedema?
We do not publish prices. The cost depends on the extent of your lipoedema, the areas treated and the number of operations. You receive a quote after the consultation and examination, once we have agreed on the plan. Compression garments and lymphatic drainage massage afterwards are not usually included.
- The areas (legs, arms), the volume removed and the operating time.
- The hospital stay and anaesthetic care.
- Compression garments and lymphatic drainage massage afterwards, which are not usually included.
Frequently asked questions
Can liposuction cure lipoedema permanently?
Not permanently, but it keeps the condition under control for many years. Lipoedema has a hereditary basis and can partly return, for example with major weight gain or hormonal changes. Studies with 8- and 12-year follow-up show that the reduction in pain, swelling and bruising lasts, and that patients need less conservative treatment. Keeping a stable weight helps you hold on to the result.
How many operations will I need for lipoedema?
Usually one or two, rarely more. It depends on the stage of lipoedema, but mainly on body weight. In women weighing up to 70 kg, treatment is usually completed in one operation, and at 70 to 90 kg in two. At higher weights I recommend losing weight first; if that is not possible, more than two operations may be needed, for example treating the arms separately from the legs. I usually do not exceed 7 litres per operation, so that recovery remains safe.
How long do I wear compression garments after lipoedema liposuction?
For the first 10 days you wear them day and night; after that you can take them off to sleep. Daily wear lasts about 6 weeks for the thighs and upper arms and about 3 months for the calves and ankles, longer after extensive surgery. As the swelling goes down, you need a smaller size. In advanced lipoedema, compression continues long term with lighter stockings.
When can I start lymphatic drainage massage after lipoedema surgery?
Usually after week 2 to 3. Before that the skin is very sensitive and the massage hurts, without real benefit. I recommend 2 to 3 sessions a week for 3 to 4 months, always with a physiotherapist certified in lymphatic drainage. Massage, together with the compression garment and avoiding long hours standing, speeds up the resolution of swelling, which lasts longer at the calves and ankles. Later you can have it whenever your legs feel heavy.
When can I go back to work after liposuction for lipoedema?
For desk work, usually after 10 to 15 days, with a footrest under the desk to keep your legs raised. In jobs with long hours standing, such as hairdressing, pharmacy or hospital work, going back before one month is possible but risky: swelling and numbness take longer to settle. The final result does not seem to be affected, but recovery becomes more tiring. This is why we schedule the date at a time without pressing commitments.
Will I have loose skin after lipoedema liposuction?
Usually not. When an even layer of fat is left under the skin, laxity is not typical, and the skin often becomes smoother. On the upper arms, the “hanging” look is usually caused by the weight of the lipoedema itself. If laxity is already present, or after very large volumes, skin removal such as an arm lift or a thigh lift may be needed later.
When can I fly home after liposuction for lipoedema?
You can fly home once the stay near us is complete, which depends on the volume removed: 2 to 5 days for up to 5 litres, 7 to 10 days for 5 to 7 litres and more than 10 days above 7 litres. I recommend a flight of up to 3 hours, or travel by car with a stop every 1 to 2 hours. In moderate and severe cases you need someone with you for the first 10 days.
Can my follow-up be done at home?
Largely, yes. After you return home, follow-up is by video call at 10 days, 1 month, 6 months and 1 year. Any skin stitches are removed at 5 to 7 days, before you leave Greece. The aftercare that matters most happens near you: lymphatic drainage massage 2 to 3 times a week from week 2 to 3, for 3 to 4 months, with a certified physiotherapist, and compression garments for 6 weeks above the knee and 3 months below it. If you have a second operation, we see you again for it 3 to 6 months later.
References
- Faerber G, Cornely M, Daubert C, et al. S2k guideline lipedema. J Dtsch Dermatol Ges. 2024;22(9):1303–1315.
- Herbst KL, Kahn LA, Iker E, et al. Standard of care for lipedema in the United States. Phlebology. 2021;36(10):779–796.
- Baumgartner A, Hueppe M, Schmeller W. Long-term benefit of liposuction in patients with lipoedema: a follow-up study after an average of 4 and 8 years. Br J Dermatol. 2016;174(5):1061–1067.
- Baumgartner A, Hueppe M, Meier-Vollrath I, et al. Improvements in patients with lipedema 4, 8 and 12 years after liposuction. Phlebology. 2021;36(2):152–159.
- Dadras M, Mallinger PJ, Corterier CC, et al. Liposuction in the treatment of lipedema: a longitudinal study. Arch Plast Surg. 2017;44(4):324–331.
- Wright T, Babula M, Schwartz J, et al. Lipedema reduction surgery improves pain, mobility, physical function, and quality of life: case series report. Plast Reconstr Surg Glob Open. 2023;11(11):e5436.
- Sandhofer M, Hanke CW, Habbema L, et al. Prevention of progression of lipedema with liposuction using tumescent local anesthesia: results of an international consensus conference. Dermatol Surg. 2020;46(2):220–228.
- Witte T, Dadras M, Heck FC, et al. Water-jet-assisted liposuction for the treatment of lipedema: standardized treatment protocol and results of 63 patients. J Plast Reconstr Aesthet Surg. 2020;73(9):1637–1644.
- Hoffmann JN, Fertmann JP, Baumeister RG, et al. Tumescent and dry liposuction of lower extremities: differences in lymph vessel injury. Plast Reconstr Surg. 2004;113(2):718–724.
Consultation
In Thessaloniki, in Athens or by video. Examination, options and a written plan.